What Actually Happened to People Who Underwent Lobotomy? HH

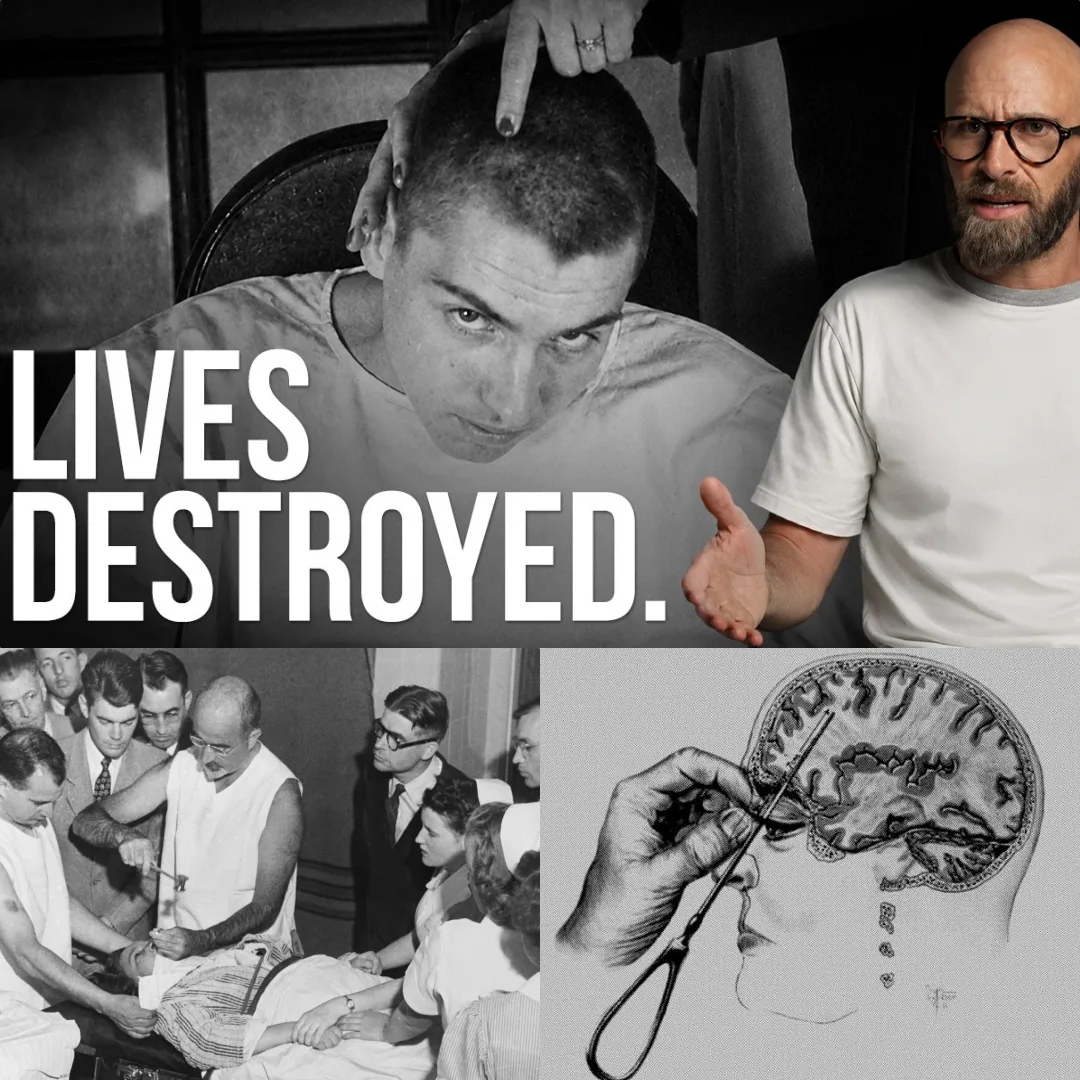
On the 17th of January 1946, 29-year-old Sally Ellen Yanesco was placed on a table in Washington DC and knocked unconscious with an electrically induced seizure. Holy, you not heard of anesthetics, my man. Then a man by the name of Walter Freeman lifted one of her eyelids, positioned an ice pick beneath it, literally just an ordinary ice pick, and hammered the point through the wafer thin bone at the top of her eye socket.
He then pushed it several centimeters up into the white matter behind her forehead, swept it from side to side, and pulled it out. It was a procedure that took me minutes, and when UNESCO woke up, she was sent home in a taxi. No real after care to speak of, nor any real period of observation, either. Here, however, the matter gets all the more complicated.
Because we know what you’re thinking. This is barbarism. It’s butchery. It sounds like bloody torture or something like that. And yet, according to UNESCO’s daughter, the procedure worked a treat. Because before the procedure, UNESCO had been terribly depressed, fighting a losing battle with psychosis and violently suicidal.
And after it, all those behaviors stopped basically immediately, almost as if a switch had been flicked in her head that simply turned the suicidal behaviors off. In fact, UNESCO herself, mulling it over decades after the fact, still referred to Freeman as quote, “A great man.” And this speaks to a core and frankly quite uncomfortable reality that while we are quick to dismiss libotoies as naught but crankery of times past in the modern day, the reality is that they were complicated.
Because yes, as popular imagination posits, some patients did die shortly after their surgery. Some did find every meaningful facet of their personality torn away from them, and some did afterwards live in only the most abstract sense of the word. unable to speak, unable to walk, and existing essentially as a body on base instinct autopilot.
But then there’s the UNESCO of the world for those whom by every metric you could conjure up, labbotoies genuinely seem to have worked and worked well. And indeed, [music] it is this complicated and multifaceted reality that we’re going to be wrangling with today as we ask ourselves what actually happened to people who underwent labbotoies.
Now, the first thing that we need to do is grab the notion of crankery by the horns and see it properly put to bed. Because yes, labbotoies are not performed in modern medicine. But that does not mean that they were the result of pseudocience or the fever dream of some crank only tangentially connected to reality.
Instead, they were a real and genuine attempt to answer a question that had no easy answer back then. What the hell are you meant to do with someone who is being destroyed by their own mind when absolutely nothing that you do seems to help them in any way? Because you think mental health provisions bad now? Try turning the clock back a century or so.
At least now, generally across the bulk of the developed world, various cocktails, medication, therapy, and specialist care are available for someone suffering from psychosis, severe depression, or crippling obsessive thoughts. Then though, it wasn’t that they weren’t offered, it was that they just didn’t exist. basically at all.
John Cade’s modern use of lithium to treat mania for example came about only in 1949. Chloromromazine the first effective antisycchotic only reached psychiatric patients in 1952. And it was only in 1957 that Swiss psychiatrist Roland reported the anti-depressant effect of a pramine the first triccyclic anti-depressant.
Triccyclic being a compound that takes its name from the three rings of its chemical structure. and specialist care. Far from consisting of carefully monitored medication and talking therapies like today, back then it often meant sedation, physical restraint, prolonged baths, or simply keeping somebody locked away in lie of any better idea.
Not to say that they weren’t trying to improve things, because they absolutely were. Consider insulin coma therapy, which deliberately crashed a patient’s blood sugar, metrosol, which induced violent convulsions, and electrocomvulsive therapy, or ECT, which used electricity to trigger a seizure. But all of those either didn’t actually work or didn’t work well enough in their contemporary primitive form.
ECT, for example, was first rolled out in 1938 and genuinely did help some patients with severe depression. And indeed, a greatly modified version of it persists to this day, administered under general anesthetic with muscle relaxants, constant monitoring, and precisely controlled electrical pulses. The rest, though, less effective. Take Metrazol.
It generated plenty of dramatic early success stories. But a 1940 study published in the American Journal of Psychiatry following 320 patients found improvement rates lower than those claimed for spontaneous remission and the convulsions it induced also fractured long bones and vertebrae with an alarming regularity.
And insulin coma therapy in 1957 a control trial published in the Lancet found that patients treated with insulin coma fed no better after 6 months than those who were simply knocked unconscious with barbituates. It was, to be blunt, the flinging and seeing what stark period of mental health care. And so it was that labbotoies entered the scene.
A desperate solution when nothing else seemed to work. And indeed, a solution was needed because, contrary to what your well-meaning but reality disconnected boomer granddad believes, mental health issues aren’t something that suddenly just appeared due to a softening among recent generations. Spoiled as we are by not getting the kicked out of us by our high school teachers and not being sent down a coal mine at the age of seven, mental health issues have always been a thing.
Put it this way. In 1955, 550,000 people in the United States.34% of the entire nation’s population were housed in state mental hospitals with many institutions being overcrowded, understaffed, and functioning less of places of treatment as more as warehouses for the unwell. Not that labbotoies were wholly pioneered in this period.
They actually emerged in the late 19th century, specifically in 1888 when Swiss psychiatrist Gotautly Burkhart removed pieces of cerebral cortex from six patients. Of those six, one died and several of the others suffered seizures or aphasia, an impairment of speech and language. He published his results in this 1891 paper, and the response from his peers was uh not exactly what you’d call positive.
Take British psychiatrist William W. Ireland as an example who reacted in sardonic fashion by saying he would refer readers to the original paper quote should any English physician have the hardyhood to imitate Dr. Birkhart’s apparative procedures and it turns out that basically no physician did English or otherwise. Thus the idea remained largely unexplored for another 45 years.
But then in 1935 American neuroscientists John Fulton and Carile Jacobson presented experiments on chimpanzees whose frontal loes had been removed. One of them Becky had become frantic over mistakes. And after the surgery that proclivity vanished. Suddenly, in an instant, chopping out parts of the brain had stopped being whack Dr. Crankery.
The timing couldn’t have been better for a Portuguese neurologist by the name of Antonio Agash Monish, because he was already of the belief that mental illness might be sustained by fixed unhealthy circuits inside the brain. So, given the chimpanzeee experiment, what had previously been little more than a hunch suddenly seemed to Manish to have evidence behind it.
sever the white matter connections linking the frontal loes to the rest of it and perhaps those destructive thoughts would break too. Next, naturally came his own human experiment. It happened on the 12th of November 1935 and saw neurosurgeon Pedro Almeida Lemur working under Monish’s direction, drilling holes into the skull of a 63-year-old Lisbon local.
Alcohol was then injected to destroy the frontal white matter. And over the following weeks, the pair repeated the procedure on six more people, steadily increasing the dose as they went. Later, the pair would also develop the lucatome, a probe with a retractable loop rotated inside the brain to cut cores of tissue.
And a quick terminology point here while we’re clarifying things. Lucottomy and lobotomy do have slightly different technical meanings, but the terms have long since been used near interchangeably, which incidentally is exactly how we’ll use it today. Then, well, more. By February 1936, 20 patients in all have been treated by Manish with him declaring seven of them as recovered.
A further seven improved and the remaining six as [music] unchanged. Right now though, let’s slam the proverbial hype trains brakes on because we need to be also very clear. Even by the standards of the day, this was not the best science. There was no control group. Follow-up was short, like 11 days short. And those outcomes were very generously proclaimed with Manish declaring his very first patient cured despite her never actually leaving the mental hospital.
But these were desperate times as we have explained. And so when one Walter Freeman, a name that should be ringing a bell, got hold of the results, he cared not for their shortcomings. He was going to make progress. Based on what you just heard, do not assume that Freeman was a crank because he was anything but. What he absolutely wasn’t, however, was a surgeon. Instead, he was a neurologist.
In fact, he was a really, really good neurologist. So good, in fact, that in 1924, aged only 28, he was placed in charge of all the laboratories at St. Elizabeth Hospital in Washington DC. So yeah, once again definitely not a crank. What he was though was wildly ambitious and self-confident.
So when Manish’s early results reached him, 20 loosely graded cases mattered less than the possible reality. They teased an actually effective and reliable method for treating mental ailments. He had help too, specifically in the form of James Watts, a neurosurgeon who brought the practical skills needed to hopefully realize the man himself’s vision.
And on the 14th of September 1936, the pair performed both their and America’s first ever prefrontal labbotomy on 63-year-old Alice Hood Herat. Together, they drilled six openings into Hammet’s skull and used Manise’s lucatome, inserting it through the openings and rotating it to cut a series of spherical cores through the white matter of both frontal loes.
That took around 4 hours in all. Then Hammet opened her eyes. As for whether or not it was actually a success, it depends on when you were asking. Because by 1936 standards, it was a knock out of the park. An absolute blinder. Job most definitely a gooden. Within mere hours, her terror and agitation had seemingly vanished.
Then within a month, she was back home and managing the essentials of daily life and avoided the institutionalization that she had previously been facing. Years later, in fact, her husband even stated that she had never been happier. By modern assessments, however, well, none of that actually matters because on the fourth day, she developed a temporary stuper, weakness down the right side of her body, and a fasia.
Her personality also changed marketkedly with Freeman and Watts describing her after surgery as rather shrewish and demanding with her husband, outspoken with her friends, and unself-conscious with indolence and abusive tendencies, also developing further down the line. There was also a convulsion some months after surgery, too, during which she fell and broke her wrist.
In fact, it even turns out that newfound managing of life’s daily essentials wasn’t all that either because it was actually her maid and her husband doing the vast bulk of the work in the home. None of that mattered at the time, of course. Remember when we said how royally up mental health treatment was back then? Yeah, that procedure had gotten her out of the institution.
So, great success so far as Freeman Watts and indeed the medical world were concerned. Over the following years, the pair then refined the procedure. Mon’s lukew was discarded. Six openings became two and through each of them Watts inserted a narrow blade sweeping it through the frontal white matter to sever the connections within. It was quicker, cleaner, and more precise supposedly.
Still though, this was major brain surgery. About as major as you could ever get, in fact. Quite literally cutting through the skull and carving up what is housed within. Anything referred to as sweeping and brain surgery. Holy that doesn’t sound precise. That in itself created a problem though because major brain surgery which you believe it requires some serious talent to pull off even for a gong procedure and there just weren’t enough real neurosurgeons floating around America never mind the mental health care sector specifically to begin
rolling labbotoies out of the scale actually needed to fix the dire backlog in the nation’s mental institutions. No two ways about it then. The procedure had to become faster, cheaper, and above all else, simpler than it already had been. So simple in fact that those precious few neurosurgeons could be dispensed with altogether and the procedure could be performed by ordinary state hospital psychiatrists instead.
And a way to do exactly that was found thanks to the Italian psychiatrist Amaro Famberti. Famberty had reached the frontal loes through the thin bone above the eye socket injecting alcohol or formulin into the brain. This via the eye sockets method being known as a transorbital labbotomy. Freeman simply kept the root but replaced the chemicals with cutting, initially experimenting on cadaavvers with literal ice pickicss taken from his own kitchen.
Then on the 17th of January 1946, he attempted it on a living patient, Sally Ellenco. We already know about her, of course, having met her in the introduction to this video, so we won’t retread old ground by going over her actual procedure again. But we will say that the icepic did not become a permanent fixture.
You see, it was a temporary measure only. And it was replaced in 1948 by the Orbiter class, a thicker, stronger, icepick-shaped steel instrument originally manufactured for Freeman by Washington machinist Henry A. At marked along its shaft to show exactly how deeply it had entered the brain. And the wider medical establishment, far from recoiling in horror at it all, it was embracing labbotomy at almost every level.
In 1947, for example, Britain’s Board of Control, the government body responsible for overseeing mental hospitals, published an official report examining 10,000 procedures across 45 institutions. And as per this report, 35% of patients were discharged and another 32% improved with a report describing the behavioral changes among otherwise hopeless cases as remarkable.
And do take that with a pinch of salt, however, as we’ve already seen how success was judged back in those days. Then in 1949, proof of institutional acceptance if there ever was any, manise received the Nobel Prize for discovering the therapeutic value of lucottomy in certain psychosis. That is, he got a Nobel Prize for pioneering labbotoies.
And Freeman’s simplified version wasn’t exactly overlooked by his peers either because in 1950 after 74 procedures by his method, two American State Hospital doctors concluded in the American Journal of Psychiatry that quote, “It may be concluded that transorbital labbotomy is simple, safe and inexpensive.
In particular, it is to be recommended for institutional use.” So yes, government authorities, major hospitals, respected medical journals, and the Nobel Institution itself, all of them treated cutting connections inside the frontal loes as legitimate medicine. James Watts, of all people, was not very happy, though.
Not to say that he was having his own I have become death, the destroyer of frontal white matter moment. No, not at all. It was merely the direction Freeman was taking in which he found [music] problems. To him, you see, the bottomies remained major surgery. And so to hand it over to lowly psychiatrists of all people was an infraction of medical ethics.
Because what if it went wrong? The victims of sorry the patients could end up paralyzed, incontinent, suffering seizures, profoundly impaired, or simply dead. Perish the thought. Thus, they found themselves on opposite sides of the debate with a 1950 onwards edition of their jointly penned book, Psychoso Surgery, that being the umbrella term for brain surgery intended to treat mental illness, seeing the pair simply admit that they had been quote unable to reach an agreement.
Not that the disagreement dampened Freeman’s enthusiasm. Oh, contrary. In fact, he was just getting started because he then traveled between institutions, demonstrating the procedure, training other doctors, attracting journalists, and occasionally performing it with an instrument in both eye sockets at once. His own daughter would even describe him as the quote Henry Ford of lobotomy.
Although we do wonder if she would stand by that nowadays after the practice fell out of favor. It wasn’t just him either, because labbotoies across America were exploding in frequency as more and more people and institutions got on board with the practice, rising from roughly 150 in 1945 to 5,074 in 1949, a more than 30fold increase in just 4 years.
And those were just the annual figures. A 1951 paper published in the Archives of Neurology and Psychiatry counted more than 2,000 American labbotoies by March 1947, around 5,000 by June 1948, and more than 10,000 by October 1949. Then on top of that, a nationwide survey presented at a 1951 conference claimed there had been at least 18,600 psychosurgical operations across the US with state mental hospitals serving as the procedures primary site.
As for a final American total, well, actually, nobody has one. Records are incomplete. Repeat procedures were counted inconsistently, and the term labbotomy covered several related operations. But most estimates land well into the tens of thousands, commonly around 40,000 people, with some climbing as high as 50,000.
It’s also worth stating explicitly that as much as the lobotomy story is an American-dominated one, thanks to the work of Freeman and Watts in pioneering the procedure and Freeman himself for selling them with all the restraints of a town crier, it’s not exclusively an American one. We’ve already seen Portuguese and British aspects to it, for example.
And sure enough, that British Board of Control report covering a thousand procedures that we just mentioned, well, it barely scratched the surface of the situation because when the Ministry of Health later counted the procedures performed across England and Wales between 1942 and 1954, so not even the whole of the UK, it identified 10,365 people who had undergone a single lucottomy, plus another 462 who were operated on more than once.
Crucially too, 84% of those British operations were the standard drilled skull variety, not transorbital. So, it’s actually fair to consider that method something of an Americanism, even if lobotoies were at large, were not. And indeed, it goes on when we start looking towards Scandinavia. Sweden, for example, lobbotomized around 4,500 people.
Norway somewhere between 2500 and 3,000. Finland roughly 1,600, and Denmark more than 4,000. the latter likely giving it the highest rate per head of any country in the world. Nor did the procedure stop at Europe’s borders either because by 1949 around 2,000 Japanese patients had undergone some form of psychoso surgery while Brazil would ultimately operate on more than a thousand patients too.
From there the numbers become increasingly difficult to pin down. Different countries use different definitions. Many kept incomplete records and some patients were operated on multiple times. There is therefore no genuine exact [music] worldwide total. But according to medical historian Yaspervati Krag writing in his 2021 book Labbotomy Nation the history of psychosurgery and psychiatry in Denmark by 1956 somewhere between 60 and 80,000 people worldwide had undergone lobotomy or one of its closely related psychosurgical variants.
So within little more than two decades an experimental operation performed on 20 Portuguese patients had become an internationally accepted form of medicine practiced on every inhabited continent. Now however we find ourselves with a problem because while zooming out and having a look at the wider story and context is vital if we wish to gain a full and complete understanding of the matter such a lens does invariably dehumanize it all rather people’s individual experiences and indeed suffering come up only as exemplary
evidence to broader trends but there wasn’t just one Sallyenko and one Alice Hood Hammet was there were perhaps as many as 80,000 of them each with their their own illness, family, life and results. So then with that said, let’s now zoom back into those individuals themselves and in fact to the very question we posited back at the start of today’s episode.
What actually happened to people who underwent labbotoies? And the answer to that, well, it can only be a vague and nebulous one. Put it this way, the closest thing that we have to a decent well sampled self-reporting study from the patients themselves comes from 1956 when doctors Alorn and Elliot Slater published prefrontal lucottomy views of patients and their relatives in the British Medical Journal.
As for what they said, their original group contained 118 patients, not huge admittedly, but we’ve got to work with what we’ve got. Five of whom died as a direct result of the operation. Then after further losses and exclusions, 103 survivors who could actually be asked what they thought remained. And of those, 66 in all said that they were glad they’d undergone the operation.
Half of which again went so far as to say they were very glad that they’ undergone it. Then there were another 23 who were neither glad nor sorry, 11 who regretted it, and three who considered it a great mistake. Also included two were the verdicts of some of their relatives. And of the 93 questioned, 72 thought their family member better, 10 saw little to no difference, and 11 thought they had been proactively made worse.
So surely we have an easy verdict then, right? Because after all, these are the patients themselves. So no contextual flim flam here. They were feeling about it, they would tell us. Well, just hold that thought actually because that was just their initial take. Later, 43 of the patients also reported both unpleasant and unwelcome changes in themselves, as did 51 of their relatives.
Chiefly reported were irritability, emotional flatness, lethargy, memory problems, reduced intellect, and tactlessness. All while many of those same people still considered the exchange worthwhile. One patient, if you could believe it, even regarded reduced emotional responsiveness as a benefit. Then there was another who acknowledged having a poorer memory post labbotomy but didn’t consider it an issue because it had merely fallen from phenomenal to normal.
And then there were the patients who thought they were better while their relatives thought them worse alongside an even larger group where the opposite applied. The paper’s overall conclusion then came down to a question, not a simple one at all, but a variation of the question that you’re all likely now asking yourselves.
By what standards are we to say that one opinion is right and the other is wrong? And actually, if you ask us, they reached about as nuanced an answer as they could reasonably be expected to reach. Because, as they then went on to say, quoting, “Any particular change of personality cannot be regarded as good or bad in itself, though there are some changes such as irritability whose effects are nearly always bad.
With most changes of personality, there are both good and bad sides to its effects. All that is observationally possible is to say whether the patient as a whole has benefited or suffered. Even this is a question which can only be answered in a defined context. There are patients who consider themselves better and are considered worse by their relatives and a more numerous group to which the opposite applies.
By what standards are we to say that one opinion is right and the other wrong? It is emphasized that the assessment of the value of a lobotomy operation to the patient is a subjective one whoever makes it. And it is pointed out that in the past the patient’s opinion has tended to take second place to that of the medical investigator.
So, you can probably see what we mean. But ultimately, maths can take us only so far. If we want to truly know what happened to people who underwent lobotoies, we need to stop looking at the numbers and meet the people they represented. We’ll start with an anonymous woman identified only as case 42 in Freeman and Watts’s psychosurgery book.
She was 28 years old, married, mother of three children. She also developed a vicious obsessive illness centered upon suicide. Not merely an urge to kill herself, but the terrifying belief that if she did, she would have to kill her children, too. 6 weeks in a state hospital had totally failed to help her as two had a course of then standard shot treatment.
And so it was that on the 16th of September 1938, Freeman and Watts performed a standard prefrontal labbotomy, one of the drilled skull ones rather than the later eye socket shortcut, if you recall. 5 weeks later, the woman described herself as rather laxidasical, but said that the suicidal drive had totally disappeared.
Then after 3 months, she was driving again, managing a household, entertaining visitors, and had even prepared Thanksgiving dinner for her family and five guests. Not that she was entirely still herself, however. Her memory and concentration were poorer. She found planning difficult, procrastinated more, and sometimes struggled to translate her intentions into actual action.
Jesus Christ, don’t we all? Further, by 9 months post-operation, she’d gained 25 lbs, still required pushing into certain activities, and could become angry when she was pushed. Her emotional extremes had also flattened. Less unbearable misery certainly, but less intensity in the opposite direction, too. 2 and 1/2 years later, however, she remained free of suicidal thoughts, was active in her church, helped with the Red Cross, attended PTA meetings, cared for her family, and reported never feeling unhappy. Then, almost 9 years after the
operation, she wrote that her health was excellent. She was doing her own work and remained active across numerous community organizations. Even her husband reportedly regarded her as more normal than had ever known her. And perhaps unsurprisingly, her own verdict, when all things have been considered, was that quote, “The benefits certainly outweigh any handicaps.
” Now, huge pinch of salt here. This was an anonymous case selected by two committed advocates for inclusion in their own book. There was also no control group, no independent examiner, and no way of knowing what might have happened without surgery. But her opinions and her words were still her own.
And who are we to take them away from her by the only standard that truly mattered to her, whether she would rather live as the woman she had become than die as the woman she had been. The operation had worked. And then we get to the case of the then 36-year-old Patricia Men, who reached the limit of her battle with her demons in 1962 and attempted suicide by ingesting an entire bottle of pills, an act that brought her into the charge of Freeman.
Patricia later remembered him warning her in brutally explicit terms that she might emerge profoundly disabled or that she might die. She was so miserable, however, that she cared not and thus consented to a labbotomy. What happened immediately afterwards is largely absent from her memory. She could remember meeting Freeman, but not the hospital, the procedure, nor her initial recovery.
According to her husband, Glenn, though, she announced on the journey home that she wanted a divorce, something Patricia herself flatly had no recollection of ever saying. Glenn himself would also later claim that most aspects of her personality remained unchanged, except that she was much easier to get along with.
And yes, there it is again, improvement being measured partly by the comfort of everyone around the patient. But Patricia herself held the same positive verdict. She returned to cooking, shopping, managing the household and later summarized the result in six simple words and will quote her, “I went home and started living.
” The pair remained together and Glenn eventually described himself as delighted with the outcome. As far as they were concerned, they had enjoyed a good life and it was all thanks to the lottomy. So there it is then, two cases, call it three if we add Salel and Ico from the introduction to the pile two in which both the patients and their families believed the operation had helped.
And it actually appears as though it did. Not perfectly, of course, and certainly not without some costs and losses, but still it helped. It left them in a better state than in which they had started. Then, however, we get to the less clear-cut cases, the ones who outwardly did appear to be helped by their labbotomy, at least in so much as their targeted symptoms were lessened, but for whom the costs started to really stack up to an eyebrow raisingly large degree.
Take Anna Ruth Channels as an example. She was a young wife and mother, still only in her mid-20s, who was referred to Freeman around 1950 after suffering from truly terrible headaches for many years. We haven’t missed any details there either. The publicly available records make no mention of any psychosis, violent behavior, or suicidal depression, any mental ailments at all, basically just headaches that seemingly would not go away.
All the same though, Freeman Solution was a transorbital labbotomy. When you’re a hammer, all you got is nails. And remarkably enough, according to Anna’s daughter, Carol, it actually worked. The headaches disappeared. Better still, Anna stopped worrying. Not something that was initially given as a problem, but that was simply reported as a benefit post surgery.
It’s a problem, though, because upon returning home, Anna could no longer manage even the most basic acts of adult life. Her sister had to retach her how to bathe, how to use the toilet, everything basically, right from the very beginning. She could also no longer properly care for her children, with Carol and her sister subsequently spending portions of their childhood in foster homes.
Bizarrely though, it was not as though the LME had rendered her dim-witted. Far from it, in fact, because Anna became astonishingly good at pinball, and at carnivals, she could glance at a jar filled with pennies and estimate the number inside with remarkable accuracy. As Carol herself would later sum up in a 2005 interview with labbotomy survivor Howard Dully for the radio documentary My Labbotomy, quote, “She was so smart, but she had no place to put it.
” And indeed, as much as Carol genuinely loved Anna, describing her as a wonderful playmate and a best friend. The labbotomy and the subsequent changes to Anna’s psyche ended up totally destroying their relationship as mother and daughter. As Carol again remembered it, quote, “I never remember calling her mama.” This case is peak middle category.
Then the labbotomy did exactly what it was intended to do, dealing with Anna’s headaches. But when it came at that cost, her independence, judgment, social boundaries, and ability to function as a mother, who nowadays would be able to say that it was a success with a straight face. Nor was Anna’s case some freakish one-off either.
Take the anonymous British case G, documented by psychiatric social worker Mary A. Lane in her 1956 paper, The Effect of Lucottomy on Family Life. Lane’s perspective is particularly valuable here because she was not standing inside a hospital judging whether patients had become calmer, quieter, or easier to nurse. She was instead following women after they had returned home and examining what their supposed clinical improvement actually did to their relationships.
And Case G had by the standards of the treatment improved because beforehand she had suffered from severe obsessive and phobic symptoms. And it was actually her own husband who insisted that she undergo a libotomy. And sure enough, following the operation, those symptoms totally disappeared. Target located, target destroyed. Great success.
Except the woman who returned home, was now lethargic and displayed what Lane described as a quote inappropriate emotional response to situations. Sound familiar? And it gets worse, too, because her husband, the very husband who had demanded she get the procedure, then became furious with her emotional changes, eventually throwing her out of the house and refusing to allow her to see their son.
Devastating would be the only word for this. And yet, outwardly, it was a successful labbotomy. Because had the symptoms been dealt with? Yes. Yes, they had. The catastrophic collapse of one’s life at the hands of a domestically abusive maniac, however, no, not so much. Although perhaps we’re hyperbolizing the story just a tad too much here because reactions such as Anna’s and Case G’s were a known about thing at the time.
Freeman and Watts even had a term for it in the 1950 second edition of psychosurgery so-called surgically induced childhood. Then in his 1951 paper personality in the frontal loes Freeman was blunt still carried sufficiently far towards the back of the frontal loes the operation could reduce a patient to the social level of the four-year-old child.
Neuros psychiatrist Kurt Goldstein had made a similar point the year before too. In his February 1950 Scientific American article, Prefontal Labotomy Analysis and Warning, conventional intelligence tests could make a patients intellect appear relatively unchanged, even as their ability to think abstractly, make adequate choices, take the initiative, and shift voluntarily from one task to another had been badly impaired.
And of course, don’t forget those were just the ambiguous cases. Because Anna’s headaches had disappeared, Case G’s obsessions and phobias had been put to bed. A part of the intended bargain, however obscenely expensive, had still been delivered. Others, they didn’t even get that. They were just simply destroyed by the procedure.
Take Buler Jones. Around 1949, following the birth of her third child, Buler began hearing voices and developed the delusional belief that she was the lost queen of Scotland. Then with none of those symptoms having particularly improved, she was committed to Pilgrim State Hospital in New York where doctors attempted 15 rounds of ECT over the course of 10 weeks.
And when that didn’t work, she was recommended for labbotomy. Just one of 12 patients operated on at that institution that day after 6 months of observation, still delusional, no improvement at all. still claiming to be the lost queen of Scotland, still displaying the behaviors that had gotten her institutionalized in the first place, and still considered too unwell to be discharged, with her also being subsequently transferred to a ward for supposedly untreatable patients.
Not that there hadn’t been any change at all, though, because oh boy, had there been change. She could no longer, for example, sit down and read, and neither could she write. Her long-term memory had also gone. Her emotional expression had flattened, and she appeared to exist almost entirely in the immediate moment.
As her daughter Janice Jones Thompson would later remember it in an interview for PBS’s The Labotamist, quote, “There was no change in her behavior other than she lost her higher intellect.” And that really is it, isn’t it? No silver lining amidst the cloud. No difficult, was it really worth it equation to be grudgingly worked through, just the straightup destruction of everything she had ever been as a sapient being, and not a single change to her mental ailments.
Worth noting too, Buler also never went home. She remained a pilgrim until 1972, two full decades after she had first been admitted and continued requiring institutional care afterwards. As Janice later put it, “We were told she’d be away for 6 months. Then a year passed, then 10. We gave up hoping.” And then, of course, there is the disastrous lobotomy, the one you likely already knew about before even clicking on this video. That one of Rosemary Kennedy.
Now, we need to put a common myth to bed here because Rosemary was not a completely healthy young woman who was subjected to brain surgery purely because her father found her embarrassing, as some retellings posit. Instead, [music] she had experienced developmental and learning difficulties throughout her entire life, and by her early 20s was becoming increasingly irritable, aggressive, and psychologically troubled.
But she could still walk, talk, write letters, attend dances, perform basic arithmetic, participate in family life, and maintain relationships with the people around her. Her teenage diaries recorded concerts, dances, meetings, and even a visit to the Roosevelt White House. When her father became the American ambassador to Britain, she was even presented at court alongside her mother and sister.
She had difficulties, make no mistake, but she actually had a life and indeed a self. That’s the takeaway. But then in November 1941, when she was aged only 23, her father, Joseph Kennedy, authorized Freeman and Watts to perform a prefrontal labbotomy. Not the icepic procedure, the older drilled skull one. The most detailed account comes from Watts himself speaking more than half a century later, so an appropriate pinch of salt is needed, who recalled that Rosemary was probably awake under mold sedation.
Not that that was an overly difficult deduction, because as he told it, Freeman spoke to her during the procedure and attempted to judge the damage being done through her responses, asking her to recite prayers, sing familiar songs, count backwards, and answer questions. and their method for determining when they had cut far enough.
In what’s his own words, quote, “We made an estimate on how far to cut based on how she responded.” Then, when Rosemary began becoming incoherent, they stopped. But by then, it was too late. The damage was done, and it was immediately apparent. Rosemary could neither walk nor speak properly, and further she was incontinent, physically disabled, and totally incapable of caring for herself.
She did eventually recover some movement and limited speech and remained conscious of her surroundings, recognized her family, developed friendships, enjoyed shopping and swimming, and lived according to an established routine. But she would never regain her independence. Nearly everything a struggling but perfectly functional young woman had spent 23 years learning how to do was gone.
Even her own mother, Rose Kennedy, would later concede that although the operation stopped Rosemary’s violent behavior, it had also left her permanently incapacitated, writing that, quote, “She lost everything that had been gained during the years by her own gallant efforts and our loving efforts for her.
” Rosemary lived for another 63 years after the operation, the overwhelming majority of her entire life requiring permanent supervision and custodial care. So again, no ambiguity nor context required here because while not all labbotoies amounted to medically sanctioned devastation, as we have seen at length now, Rosemaries and indeed bulers quite evidently did.
So how did lobotoies come to an end then? Well, there was a clue in how we framed this episode actually because you know when we said that labbotoies shouldn’t really be written off as the old days medical crankery and instead should be viewed as a desperate attempt to do anything in the face of otherwise doing nothing.
Well, yeah, something else, something better did come along. That’s just the top and bottom of it. And in fact, we’ve already met that something. Clomisine, the first effective antisycchotic which reached psychiatric patients in France in 1952. But it was in 1954 the British researchers Joel and Charmian Elks provided some of the first proper controlled evidence of what the drug could do, publishing their results in the British Medical Journal.
Their study involved 26 chronically overactive psychotic patients, each of whom received chloromazine and an inert placebo at different points across 22 weeks. Not exactly the biggest sample group, but 22 weeks was at least a respectable study period. There was no separate control group, though. Instead, each patient acted as their own control, switching between chloromrozine and identical placebo tablets with neither the ward staff assessing their behavior nor the patients themselves having any idea which they were actually receiving.
And the result, seven displayed what the researchers considered a definite improvement while another 11 improved to a lesser extent. 18 of the 27 then 67% showing some kind of improvement. Several of those who responded to chloromazine also deteriorated again when secretly returned to the placebo. This was a vital turn because while 27 patients could hardly settle the question beyond all doubt, that repeated improvement and relapse pattern was strong evidence that the drug itself was really doing something. Not that it was
genuinely curing their psychosis because we’re talking very early days of antisycchotics here. So, it absolutely was not doing that. But it was making them calmer, less tense, and less distressed by their ongoing delusions and hallucinations. It wasn’t entirely harmless, though. Antisycchotic drugs do typically have a catalog of their own serious side effects.
And clromisine was absolutely no different, with its lead one being heavy sedation, dangerously low blood pressure, and Parkinson-like movement disorders. But then again, labbotoies came with their own side effects, too, didn’t they? And unlike a labbotomy, chloromine’s dosage could be altered.
If it didn’t work, another drug could be attempted. And if it started actively making matters worse, you could stop. No permanent severing of connections inside the frontal loes. No hoping that the damage had landed in precisely the right place. No discovering that you had cut too far after the patient awoke and could no longer speak.
And crucially for those overcrowded state hospitals, pills could be distributed to hundreds of patients without needing an operating theater, a neurosurgeon, or some wildly overconfident and expensive medical showman swinging a specialized ice pick around. Not that antisycchotic drugs killed the labbotomy overnight. There was no immediate switch flicking where the medical establishment writ large went thank we don’t have to do that anymore.
Hence also manise receiving the Nobel Prize eight years after Rosemary Kennedy’s disastrous procedure. Instead, the process was a gradual one. Labbotoies tapering off in popularity and antisycchotic drugs becoming ever more understood and of course available. All the while, a consensus began to gradually build that lobotoies really weren’t the done thing anymore.
One of the biggest blows to the lbotomy’s image came in 1958 when British psychiatrist AA Robin published a controlled study of the effects of lucottomy comparing 198 operated patients against 198 similar patients who had not been operated upon with both groups observed for a minimum of 5 years.
The result 84 labbotomy patients were eventually discharged compared with 80 of the controls. As Robin concluded, quote, similar patients recover after lucottomy in similar numbers to those who recover in a matched control group not so treated. And Robin’s findings were not some outlying fluke either. Because in 1964, Canadian neurosurgeon Kenneth McKenzie and psychiatrist G.
Kasanovski published another 5-year comparison, this time involving 183 operated patients and 183 controls, and again found no statistically significant difference in overall discharge rates at all. Quoting prefrontal dichotomy does not produce any rate of remission significantly beyond that to be expected without the operation.
None of this meant that case 42 Patricia M Sally Ellenco and the others who swore by their operations were lying. That’s absolutely not the case. Individual patients plainly could benefit. We have seen that for ourselves. What it meant was that once researchers stopped asking did some patients improve and instead ask did more patients improve than otherwise would have the enormous and reliable benefit promised by labbotomy advocates became really rather difficult to find.
Combine that with the deaths, seizures, relapses, emotional flattening, lost initiative, and surgically induced childhood that we’ve already discussed, and well, the bargain suddenly looked a whole lot less appealing, especially now that doctors had other options to try. For Walter Freriedman though, having built a career upon lobotoies as he had, he would be much more hesitant in getting the message, carrying them out all the way through until 1967.
In fact, because it was then that he was visited by Helen Mortensson, one of his first 10 transorbital patients whom he had initially operated upon in 1946. After suffering a relapse in 1956, Mortensson had returned to Freeman and undergone the procedure for a second time. Then, following several more productive years, she came back once again wanting a third one.
During that third procedure, however, Freeman seed a blood vessel inside her brain, fatally wounding Mortonson with a cerebral hemorrhage that would claim her life three days later. And Freeman, well, as he put it in his unpublished autobiography, quote, “This time, to my dismay, she had a hemorrhage and died in 3 days. This was the last day I operated.
” All right, so where’s that leave us? Well, if you ask us, it all comes down to a simple proclamation. I mean, thank we don’t have to do that anymore. Not because every labbotomy was pointless. every doctor involved was a crank nor even that every patient was completely destroyed by the procedure. It would certainly be an easier story. Yeah.
But as we’ve seen, it would not be the accurate story because what actually happened to people who underwent labbotoies? Well, basically everything happened. Some experienced genuine relief, returned home, resumed their lives, and remained grateful for the operation. Some escaped the specific symptom that had been tormenting them, but paid for that relief with their memory, initiative, emotional range, independence, or former place within their family.
Others received no meaningful benefit whatsoever, only intellectual impairment, physical disability, or a permanently altered personality piled on top of the illness that they already had. And some, of course, in the most tragic outcome of all, simply died. But, and this is where any conclusion gets tricky, the former two outcomes were not the result of medical crankery.
For all of the procedural flaws that we found, the odd slightly duff data set here, the occasional wildly generous definition of success there, there can be no denying the fact that lobotoies were an attempt to actually do some good in the face of ills that then appeared insurmountable. And what’s worse, they did have empirical rationale behind them.
But such is the history of medicine. It’s making do with what we’ve got until something better comes along. Surgery, for example, used to be done without antiseptic, killing god knows how many people through infection. And then Joseph Listister introduced germkilling carbolic acid to surgery in 1865. Blood transfusions were much the same, too.
Before Carl Lansteiner identified the major blood groups in 1901, pumping one person’s blood into another was basically a biological game of Russian roulette. It might save them. It might kill them. And nobody really understood why. And are Listister and Land Steiner’s forerunners butchers simply because they persevered? In fairness, yeah, possibly, depending on how you take your moral tally.
But the fundamental point still remains. Labbotoies are nothing if not a surprisingly complicated matter. So, like we say, thank we don’t have to do them anymore. Thank you for watching.








